
Sudden Deafness, Part 1: Diagnosis and Treatment
Hearing loss that occurs instantaneously or over a period of a few days without immediately apparent cause is called Idiopathic Sudden Sensorineural Hearing Loss (ISSNHL). In part 1 of this series, the diagnosis and initial treatment of this condition are described in relation to most patients’ demands for active and aggressive intervention. Part 2 (to follow in the next issue) will address rehabilitation.
Key words: audiology, deafness, diagnosis, hearing aids, idiopathic, otology, rehabilitation, unilateral and bilateral hearing loss, sensorineural.
Introduction
Rush Limbaugh's severe-to-profound, bilateral, rapidly progressive hearing loss generated considerable public interest in sudden deafness. In his case, its cause was reportedly an autoimmune disease of the cochlea.1 Diagnostically, however, many patients who suffer a sudden hearing loss are not as fortunate as the popular radio commentator. The cause of their sudden hearing loss remains unexplained.
Idiopathic sudden sensorineural hearing loss (ISSNHL) ranks high among the difficult clinical conundrums facing audiologists and otologists. Idiopathic refers to unknown etiology, and at least a third of cases of sudden hearing loss fall into this category.2 Inherently, ISSNHL imposes difficult treatment decisions on the clinician.
Much of the literature urges prompt treatment. In the face of ISSNHL’s mysterious onset and indeterminate prognosis, should rehabilitation proceed? The second instalment of this article addresses that question; here we describe ISSNHL, its incidence, diagnosis, and initial treatment.
It is estimated that between five and 25 per 100,000 persons in the U.S. will suffer ISSNHL in any given year.1 Canadian experience with ISSNHL probably does not deviate significantly from this statistic,3 although Canadians with impaired hearing differ in several demographic respects from their U.S. neighbours.4 Reasons why reported incidence rates likely underestimate ISSNHL's occurrence in Canada are that available data are for reported cases; when hearing quickly recovers, the sudden loss is not reported; and lastly, many people do not seek assistance for mild losses, even though they are sudden and unexplained.
ISSNHL's incidence is far greater in adults than children. The average age at onset is 40-50 years, with the majority of the patients over 40 years old.5 Another established relationship is that ISSNHL is 50 times more likely to be unilateral than bilateral.6,7 Only the unilateral condition is considered in this paper because of the rarity of bilateral cases.
Again, the size of the available statistics must be viewed with caution for the reasons noted above. Nonetheless, the relationships within ISSNHL will probably remain as described.
Illustrative Case Histories
On 5 March 1999, Patient A, a 61-year-old surgeon, awoke with a severe hearing loss in his right ear. His general health was excellent, and he had no tinnitus or vertigo--hopeful diagnostic indicators. His audiologic findings appear in Figure 1.
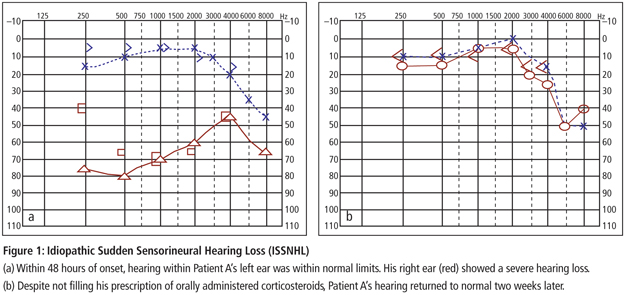
Hearing in the left ear was within normal limits. The right ear showed a severe, sensorineural hearing loss averaging 70 decibels (dB) hearing threshold level (HTL). The audiometric configuration was gently rising. His ability to understand speech was poor to absent--a prognostically bad sign.
He received a diagnosis of ISSNHL and was given a recommendation for a short course of orally administered corticosteroids. He accepted the prescription but did not fill it! Two weeks later, without intervention, his hearing returned to normal.
His case illustrates complete spontaneous recovery of hearing. Had he followed the recommendation to take the corticosteroids, an incorrect