An Overview of Delirium in the Critical Care Setting
Yoanna Skrobik, MD, FRCP(C), Director, Adult Critical Care Training Program, Université de Montreal; Associate Professor, Faculty of Medicine, Université de Montreal, Montreal, QC.
Delirium is a morbid and common complication in the critically ill patient. Its recognition is made more difficult by the inability to interview the intubated patient, and by the presence of drugs and confounding comorbidities. Delirium screening (described with the ICDSC and the CAM-ICU) with tools specifically designed for the acute care setting can help the nurse or clinician identify its presence. Risk factors for delirium in the critical care setting differ from those described in other populations. Treatment is currently empiric.
Key words: delirium, critical care, outcomes, intensive care, screening.
Introduction
Delirium in hospitalized patients is well recognized as morbid,1,2,3 costly and disturbing to patients, caregivers and family.4 Delirium in the intensive care unit (ICU) is associated with adverse outcomes such as self-extubation, removal of indwelling catheters,5 prolonged ventilator dependence6 and lengthened ICU and hospital stay.7-9 Although delirium has not been associated clearly with increased ICU mortality,5,6 it seems to be an independent marker for increased one-year mortality.10 Identification of delirium in a critical care patient, in whom sedation and analgesia affect level of consciousness, is challenging.11,12 Agitation and anxiety in the critical care setting may be due to delirium, pain or emotional distress--all are common and may mimic one another. It is not in the scope of this review to address pain and anxiety evaluation, neither of which has been well described in the critical care context as publications focus primarily on sedation.13 Delirium screening tools to facilitate identification or recognition of delirium in the ICU setting, and what is known of the disorder in the ICU, are described herein, with the goal of providing the practitioner with perspective on this important clinical syndrome.
Screening for Delirium in the ICU
Delirium, a transient neuropsychiatric syndrome, is associated with decline in cognitive function and change in behaviour. The essential diagnostic features are defined by the Diagnostic and Statistical Manual of Mental Disorders, version IV (DSM-IV), as follows:14
- Disturbance of consciousness with reduced ability to focus, sustain or shift attention.
- A change in cognition or the development of a perceptual disturbance that is not better accounted for by a pre-existing dementia.
- The disturbance develops over a short period of time and tends to fluctuate.
- There is evidence from history, physical examination or laboratory findings that the disturbance is caused by the physiological consequences of a general medical condition.
The critical care setting, which includes intubated and often sedated patients, makes it difficult to apply the DSM-IV criteria using the standard interview methods described in other populations. Recent studies have assessed evaluation methods applicable to the critical care setting. The patient's critical care context usually implies a life-threatening medical condition. The tools that have been developed recently to screen for15 and facilitate identification of delirium16 in the ICU thus base their criteria primarily on the first three elements of the DSM-IV definition.
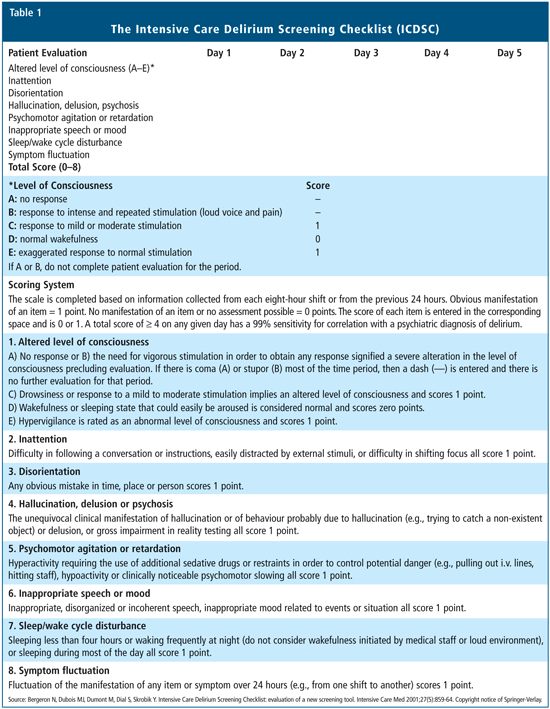
The intensive care delirium screening checklist (ICDSC; Table 1) was described in serially admitted medical-surgical critical care patients and compared to a psychiatrist's clinical diagnosis in a recent evaluation.15 Every eight-hour shift, 93 patients were evaluated with the screening tool. The mean age of patients was 62 years, the mean APACHE score was 14 and the incidence of delirium was 22%. The checklist was found to screen with great sensitivity (99%) and good specificity (64%). All patients with a false-positive screening score (of 4/8 points or more) had a structural neurologic abnormality or active neurologic disease.