
Diagnosis and Management of Asymptomatic Hyperuricemia and Gout in Older Adults
Ian K. Tsang, MB, FRCPC, Clinical Professor, Division of Rheumatology, Faculty of Medicine, University of British Columbia, Vancouver, BC.
Gout is more prevalent in older adults than middle-age adults, and it affects women almost as commonly as men. An important clinical consideration regarding gout is that while hyperuricemia is commonly associated with gouty arthritis, a diagnosis of asymptomatic hyperuricemia does not generally require treatment. In addition, the clinical presentation and course of gout in older patients differ from the typical cases of middle-aged patients. Moreover, older gout patients present a challenge for physicians who manage them because of the high incidence of comorbid conditions and the likely occurrence of reduced renal function among this age group. This article reviews the diagnosis and management of asymptomatic hyperuricemia and gout in the older adult.
Key words: gout, hyperuricemia, NSAID, allopurinol, arthritis.
Introduction
Gout is a clinical syndrome caused by an inflammatory response to deposition of monosodium urate crystals in the synovial or periarticular soft tissues. Gout is widely considered to be a disease of middle-aged men, but in fact it has an increasing frequency in men and women in older age groups. The overall prevalence of gout in the general population is 1.36% in males and 0.64% in females; however, the prevalence approaches 3.99% in people over age 65.1
Hyperuricemia is defined as a serum urate level higher than 7.57mg/dl for men and 6.03mg/dl for women. Serum urate concentration correlates strongly with serum creatinine, body weight, height, and blood pressure.2 Asymptomatic hyperuricemia has been reported in 25.8% in men and 15 % in women in North America. While gout is a common complication of hyperuricemia, it is not an inevitable outcome of the condition, and many patients with hyperuricemia never develop gout-like symptoms.
Typically, gout progresses through four clinical stages: asymptomatic hyperuricemia, acute gouty arthritis attacks, intercritical gout (with variable intervals between recurrent acute attacks), and chronic tophaceous gout. This article will discuss the clinical manifestations of the various stages of this syndrome and its management.
Clinical Features: Asymptomatic Hyperuricemia
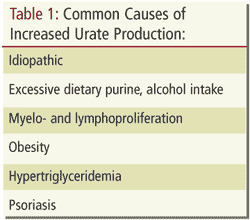
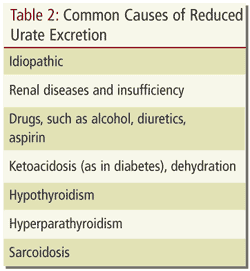
Hyperuricemia may result from increased urate production, decreased urate elimination or a combination of both (Tables 1 and 2).
Hyperuricemia has been been associated with cardiovascular disease, though it is debatable whether or not serum uric acid is an independent cardiovascular risk factor.4
The risk of gout and tophaceous gout increases with both the degree and duration of hyperuricemia. The higher the serum urate level, however, the higher the risk factor for development of gout. A serum urate level of 9mg/dl has been associated with an annual incidence of gouty arthritis of 4.9%, while the incidence rate drops to 0.5% among those with a serum urate level of 7 to 8.9mg/dl, and 0.1% among those with urate levels below 7mg/dl.3
Because most patients with hyperuricemia do not develop gout, it is unnecessary to treat patients presenting with asymptomatic hyperuricemia with urate-lowering agents. Rather, the identification of asymptomatic hyperuricemia should alert the physician to look for and treat underlying causes of hyperuricemia and associated medical conditions (Tables 1 and 2).
Acute Gouty Arthritis
A typical acute gout attack in a middle-aged person occurs after years of sustained hyperuricemia and deposition of monosodium urate in the synovial tissue (Figure 1). The initial attack is monoarthicular in about 80% of patients.6 Patients experience sudden, excruciating pain associated with redness and swelling of the affected joint. Lower extremity joints are usually affected, with about 60% of first attacks